

Menarini
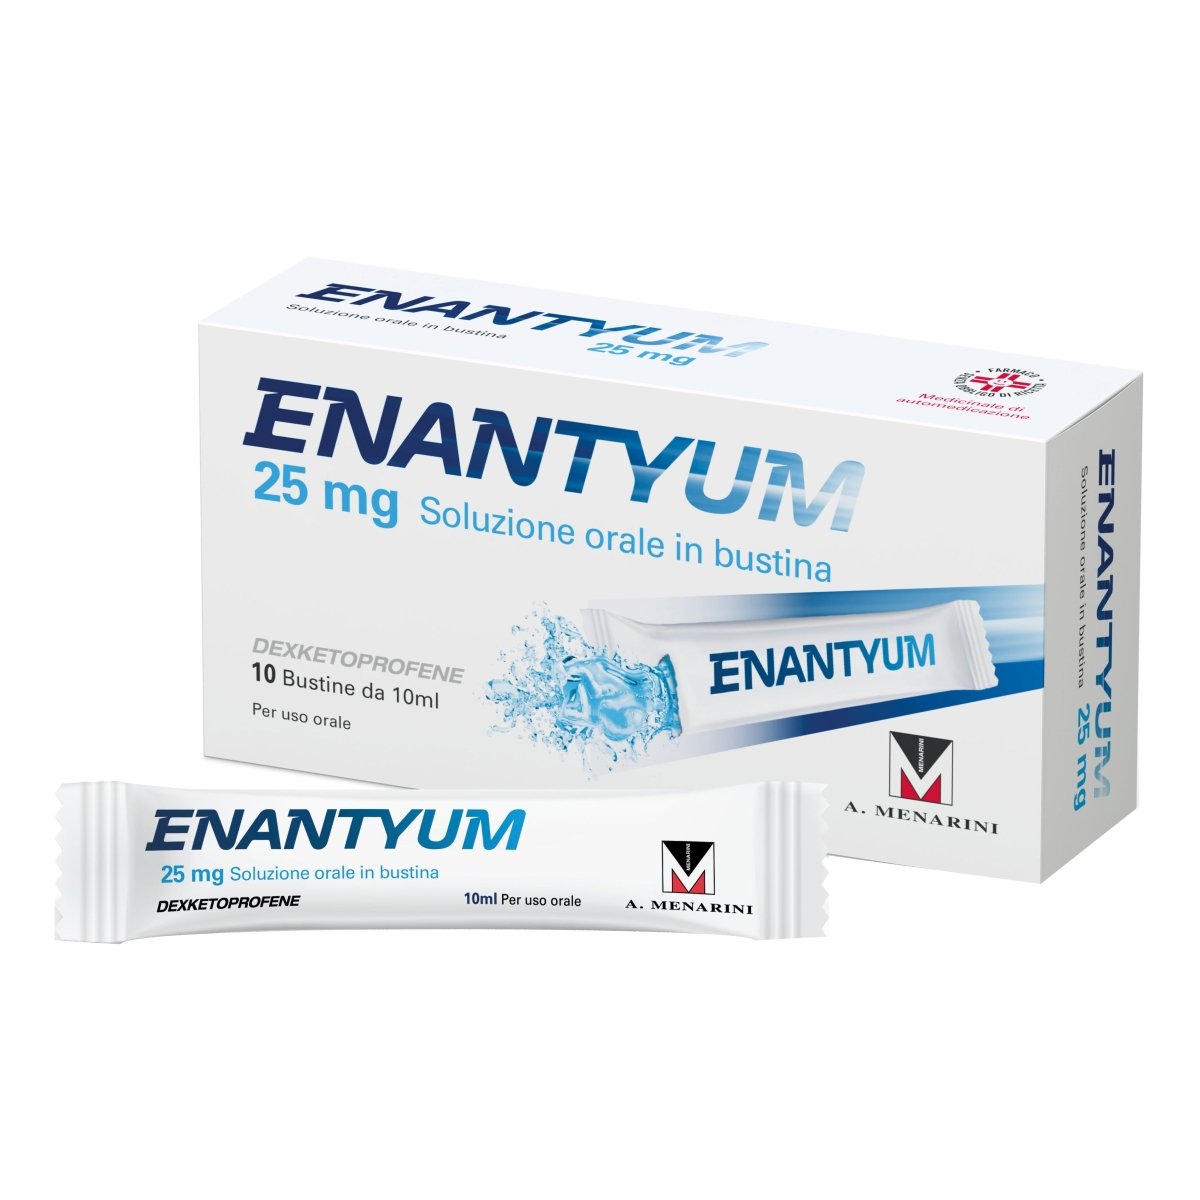
Enantyum 25 mg 10 sachets oral solution
Enantyum 25 mg 10 sachets oral solution

Couldn't load pickup availability

NET WEIGHT OF THE PRODUCT
NET WEIGHT OF THE PRODUCT
10ct
EAN
EAN
033656416
MINSAN
MINSAN
033656416
In ottemperanza all'articolo 118 “autorizzazione della pubblicità presso il pubblico” del decreto legislativo 24 aprile 2006, numero 219
INDICATIONS
Short-term symptomatic treatment of acute painful conditions of mild to moderate intensity, such as acute musculoskeletal pain, dysmenorrhea and dental pain. This medicine is indicated in adult patients.
ACTIVE INGREDIENTS
Each sachet of oral solution contains: dexketoprofen 25 mg as dexketoprofen trometamol. Excipients with known effects: 2 g of sucrose and 20 mg of methyl parahydroxybenzoate (E 218). For the full list of excipients, see section 6.1.
EXCIPIENTS
Ammonium glycyrrhizinate, Neohesperidine-dihydrochalcone, Methyl parahydroxybenzoate (E 218), Sodium saccharin, Sucrose, Macrogol 400, Lemon flavour, Povidone K-90, Disodium phosphate anhydrous, Sodium dihydrogen phosphate dihydrate, Purified water.
CONTRAINDICATIONS AND SIDE EFFECTS
- patients with known hypersensitivity to the active substance, or to any other NSAID, or to any of the excipients listed in paragraph 6.1; - patients who have developed asthma, bronchospasm, acute rhinitis, nasal polyps, urticaria or angioedema after exposure to substances with a similar mechanism of action (e.g. acetylsalicylic acid, or other NSAIDs); - patients with known photoallergic or phototoxic reactions during treatment with ketoprofen or fibrates; - patients with a history of gastrointestinal bleeding or perforation related to previous NSAID therapy; - patients with active peptic ulcer/gastrointestinal bleeding or any previous history of gastrointestinal bleeding, ulceration or perforation; - patients with chronic dyspepsia; - patients who have other active bleeding or coagulation disorders; - patients with Crohn's disease or ulcerative colitis; - patients with severe heart failure; - patients with moderate to severe renal insufficiency (creatinine clearance <59 ml/min); - patients with severe hepatic insufficiency (Child-Pugh score 10-15); - patients with haemorrhagic diathesis and other coagulation disorders; - patients with severe dehydration (caused by vomiting, diarrhea or insufficient fluid intake); - during the third trimester of pregnancy and breastfeeding (see section 4.6).
DOSAGE
Dosage The lowest effective dose should be used for the shortest duration necessary to relieve symptoms (see section 4.4). Adults: Depending on the nature and intensity of the pain, the recommended dose is generally 25 mg every 8 hours. The total daily dose should not exceed 75 mg. This medicine is indicated only for short-term treatments and administration should be limited to the symptomatic period only. Elderly: In elderly patients it is recommended to start therapy with the lowest therapeutic dose (50 mg total daily dose). The dosage can be increased to reach that recommended for adults only after good tolerability has been established. Due to the risk profile (see section 4.4), elderly people should be monitored with particular caution. Liver failure Patients with mild to moderate hepatic impairment should start therapy at reduced doses (50 mg total daily dose) under close medical supervision. Dexketoprofen should not be used in patients with severe hepatic impairment. Renal failure In patients with mild renal impairment (creatinine clearance 60 - 89 ml/min) the initial dosage should be reduced to 50 mg total daily dose (see section 4.4). Dexketoprofen should not be used in patients with moderate to severe renal impairment (creatinine clearance ≤59 ml/min) (see section 4.3). Pediatric population: Dexketoprofen has not been studied in children and adolescents. Therefore, safety and efficacy in children and adolescents have not been established and the product should not be used in children and adolescents. Method of administration Oral use. The oral solution should be taken directly from the sachet or after mixing the entire contents in a glass of water. Once the sachet is opened, the entire contents must be consumed. The concomitant administration of food delays the speed of absorption of the drug (see "Pharmacokinetic properties"), therefore in case of acute pain it is recommended to administer the drug at least 15 minutes before meals.
CONSERVATION
This medicinal product does not require special precautions for storage.
WARNINGS
Use with caution in patients with a history of allergic conditions. Concomitant use of dexketoprofen with other NSAIDs, including selective cyclooxygenase-2 inhibitors, should be avoided. Undesirable effects can be minimized by using the lowest effective dose for as long as necessary to control symptoms (see section 4.2 and the gastrointestinal and cardiovascular risks below). Gastrointestinal safety Life-threatening gastrointestinal bleeding, ulceration or perforation have been reported with all NSAIDs, at any time during treatment, with or without warning symptoms or previous history of serious gastrointestinal events. When bleeding or gastrointestinal ulceration occurs in patients receiving dexketoprofen, therapy should be stopped immediately. The risk of gastrointestinal bleeding, ulceration or perforation increases with increasing NSAID dosage in patients with previous ulcer, especially if complicated by haemorrhage or perforation (see section 4.3) and in the elderly. Use in the elderly: Elderly people have a higher frequency of adverse reactions to NSAIDs, especially bleeding and gastrointestinal perforation which can be fatal (see section 4.2). These patients should start treatment with the lowest available dose. As with all NSAIDs, before starting treatment with dexketoprofen, it is necessary to investigate previous esophagitis, gastritis and/or peptic ulcers and ensure their total recovery. Patients with gastrointestinal symptoms or a history of gastrointestinal disease should be carefully monitored for the appearance of digestive disorders, especially gastrointestinal bleeding. NSAIDs should be administered with caution to patients with a history of gastrointestinal diseases (ulcerative colitis, Crohn's disease), as these conditions may be exacerbated (see section 4.8). Concomitant use of protective agents (e.g. misoprostol or proton pump inhibitors) should be considered for these patients and for patients receiving concomitant low dose aspirin or other drugs that may increase gastrointestinal risk (see below and section 4.5). Patients with a history of gastrointestinal toxicity, especially if elderly, should report any unusual abdominal symptoms (especially gastrointestinal bleeding), particularly in the initial stages of treatment. Caution is recommended in patients co-administered with drugs that may increase the risk of ulceration or bleeding, such as oral corticosteroids, anticoagulants such as warfarin, selective serotonin reuptake inhibitors and anti-platelet agents such as aspirin (see section 4.5). Renal safety Use with caution in patients with impaired renal function. In these patients, the use of NSAIDs may cause deterioration of renal function, fluid retention and edema. Caution is required, due to an increased risk of nephrotoxicity, even in patients on diuretic therapy or who are at risk of developing hypovolemia. During treatment, adequate fluid intake must be ensured to prevent dehydration and the risk of renal toxicity. Like all NSAIDs, the product can cause an increase in blood urea nitrogen and creatinine. As with other inhibitors of prostaglandin synthesis, side effects on the kidney may occur which may lead to glomerular nephritis, interstitial nephritis, renal papillary necrosis, nephrotic syndrome and acute renal failure. Elderly patients are most at risk of renal failure (see section 4.2). Liver safety Caution is required in patients with impaired hepatic function. Like other NSAIDs, it can cause small transient increases in some liver function parameters, and also significant increases in GOT and GPT. In the event of a significant increase in these parameters, therapy must be interrupted. Elderly patients are most at risk of liver function failure (see section 4.2). Cardiovascular and cerebrovascular safety Appropriate monitoring is required for patients with a history of hypertension and/or mild to moderate heart failure. Particular caution should be exercised in cardiac patients, especially if with a history of heart failure as there is an increased risk of heart failure, given that fluid retention and edema have been reported in association with the use of NSAIDs. Clinical studies and epidemiological data suggest that the use of some NSAIDs (especially at high doses and prolonged therapy) may be associated with a slight increase in the risk of arterial thrombotic events (for example myocardial infarction or stroke). There is insufficient data to exclude such a risk for dexketoprofen. Therefore, patients with uncontrolled hypertension, congestive heart failure, established ischemic heart disease, peripheral arterial disease and/or cerebrovascular disease should be treated with dexketoprofen only after careful evaluation. Similar attention must be paid before starting long-term treatment in patients with risk factors for cardiovascular diseases (for example hypertension, hyperlipidemia, diabetes mellitus, smoking). All non-selective NSAIDs are able to inhibit platelet aggregation and prolong bleeding time by inhibiting prostaglandin synthesis. The use of dexketoprofen is therefore not recommended in patients receiving other therapy that interferes with haemostasis, such as warfarin or other coumarins or heparins (see section 4.5). Elderly patients are more likely to experience changes in cardiovascular function (see section 4.2). Skin reactions Serious skin reactions (some of them fatal), including exfoliative dermatitis, Stevens-Johnson syndrome and toxic epidermal necrolysis, have been reported, very rarely, in association with the use of NSAIDs (see section 4.8). In the early stages of therapy, patients appear to be at higher risk of onset of reactions, in most cases, within the first month of treatment. At the first appearance of skin rash, mucosal lesions or any other symptom of hypersensitivity, therapy with Enantyum should be discontinued. Masking of symptoms of underlying infections Dexketoprofen may mask the symptoms of infection, which could delay the initiation of appropriate treatment and therefore worsen the outcome of the infection. This has been observed in community-acquired bacterial pneumonia and bacterial complications of chickenpox. When this medicine is administered for the relief of pain related to infection, monitoring of the infection is recommended. In non-hospital settings, the patient should seek medical attention if symptoms persist or worsen. More information Particular caution is required in patients with: - congenital anomalies of porphyrin metabolism (for example acute intermittent porphyria); - dehydration; - immediately after major surgery. If the doctor deems long-term therapy with dexketoprofen necessary, liver and kidney function and blood counts should be checked regularly. Severe acute hypersensitivity reactions (e.g. anaphylactic shock) have been observed in very rare cases. Treatment must be stopped at the appearance of the first manifestation of severe hypersensitivity reactions after taking dexketoprofen. Depending on the symptoms, initiate the necessary medical procedures immediately, with qualified medical personnel. Patients with asthma associated with chronic rhinitis, chronic sinusitis and/or nasal polyposis have a greater risk of allergy to acetylsalicylic acid and/or NSAIDs compared to the rest of the population. The administration of this medicine can cause asthma attacks or bronchospasm especially in subjects allergic to acetylsalicylic acid or NSAIDs (see section 4.3). In exceptional cases, chickenpox may be associated with infectious complications of the skin and soft tissues. To date, a role of NSAIDs in the aggravation of these infections cannot be excluded, therefore it is advisable to avoid the use of dexketoprofen in patients with chickenpox. Dexketoprofen should be administered with caution to patients suffering from hematopoietic disorders, systemic lupus erythematosus, or mixed connective tissue disease. Through concomitant intake of alcohol, side effects related to the active ingredient, in particular those affecting the gastrointestinal tract or central nervous system, may increase with the use of NSAIDs. This medicine may cause allergic reactions (even delayed) as it contains methyl parahydroxybenzoate (E 218). This medicine contains sucrose. Patients suffering from rare hereditary problems of fructose intolerance, glucose-galactose malabsorption or sucrase isomaltase insufficiency should not take this medicine. To be taken into consideration in people suffering from diabetes mellitus. This medicinal product contains less than 1 mmol sodium (23 mg) per sachet, i.e. essentially 'sodium-free'.
INTERACTIONS
The following interactions are characteristic of non-steroidal anti-inflammatory drugs (NSAIDs) in general: Combinations not recommended: - Other NSAIDs (including selective cyclooxygenase-2 inhibitors) and high doses of salicylates (≥3 g/day): simultaneous administration of multiple NSAIDs may increase the risk of gastrointestinal ulceration and bleeding due to a synergistic effect. - Anticoagulants: NSAIDs may potentiate the effects of anticoagulants, such as warfarin (see section 4.4), due to the high plasma protein binding of dexketoprofen, inhibition of platelet function and damage to the gastroduodenal mucosa. If the combination cannot be avoided, rigorous clinical observation and monitoring of laboratory parameters are necessary. - Heparins: increased risk of bleeding (due to inhibition of platelet function and damage to the gastrointestinal mucosa). If the combination cannot be avoided, rigorous clinical observation and monitoring of laboratory parameters are necessary. - Corticosteroids: increased risk of gastrointestinal ulceration or bleeding (see section 4.4). - Lithium (described with many NSAIDs): NSAIDs increase blood levels of lithium with the risk of reaching toxic values (decreased renal excretion of lithium). Therefore, this parameter requires careful monitoring at the beginning, during adjustment and at the end of treatment with dexketoprofen. - Methotrexate if used at high doses (≥ 15 mg/week): increased hematological toxicity of methotrexate due to a decrease in its renal clearance, in general with NSAIDs. - Hydantoins and sulphonamides: the toxic effects of these substances can be potentiated. Associations requiring caution: - Diuretics, ACE inhibitors, aminoglycoside antibiotics and angiotensin II receptor antagonists: dexketoprofen may reduce the effect of diuretics and antihypertensive drugs. In some patients with impaired renal function (e.g., dehydrated patients or elderly patients with impaired renal function), concomitant administration of agents that inhibit cyclooxygenase and ACE inhibitors, angiotensin II receptor antagonists, or aminoglycoside antibiotics may cause further deterioration of renal function, which is usually reversible. If dexketoprofen and a diuretic are prescribed concomitantly, it is essential to ensure adequate hydration of the patient and monitor renal function both at the beginning of treatment and periodically thereafter. Concomitant administration of Enantyum and potassium-sparing diuretics may cause hyperkalemia. Blood potassium concentrations should be monitored (see section 4.4). - Methotrexate if used at low doses (< 15 mg/week): increased hematological toxicity of methotrexate due to a decrease in its renal clearance generally caused by anti-inflammatory drugs. Check blood counts weekly during the first few weeks of combined therapy. Increase surveillance in elderly patients and in the presence of renal insufficiency, even if mild. - Pentoxifylline: increased risk of bleeding. Closely monitor and check bleeding time more frequently. - Zidovudine: increased risk of toxicity affecting the erythrocyte lineage due to action on reticulocytes, with possible onset of severe anemia one week after starting treatment with NSAIDs. - Sulfonylureas: NSAIDs can increase the hypoglycemic effect of sulphonylureas due to saturation of the binding sites of plasma proteins. Associations to be carefully evaluated: - Beta-blockers: treatment with NSAIDs can decrease their antihypertensive effect due to the inhibition of prostaglandin synthesis. - Ciclosporin and tacrolimus: NSAIDs can potentiate their nephrotoxicity due to effects mediated by renal prostaglandins. Monitor renal function during combination therapy. - Thrombolytics: increased risk of haemorrhage. - Anti-platelet agents and SSRIs (selective serotonin reuptake inhibitors): increased risk of gastrointestinal ulcer or bleeding (see section 4.4). - Probenecid: can increase plasma concentrations of dexketoprofen; this interaction may be due to an inhibitory mechanism at the level of renal tubular secretion and glucuronide conjugation and requires an adjustment of the dose of dexketoprofen. - Cardioactive glycosides: NSAIDs can increase plasma concentrations of cardiac glycosides. - Mifepristone: there is a theoretical risk that prostaglandin synthetase inhibitors may alter the effectiveness of mifepristone. Limited evidence suggests that concomitant administration of NSAIDs on the same day as prostaglandin administration does not negatively influence the effects of mifepristone or prostaglandins on cervical maturation or uterine contractility and does not reduce the clinical efficacy of medical termination of pregnancy. - Quinolones: Animal studies indicate that high doses of quinolone antibiotics in combination with NSAIDs may increase the risk of seizures. - Tenofovir: concomitant use with NSAIDs may increase blood urea and plasma creatinine levels, consequently renal function should be monitored to monitor a potential synergistic influence on renal function. - Deferasirox: concomitant use with NSAIDs may increase the risk of gastrointestinal toxicity. When administering deferasirox with these substances, careful clinical monitoring is necessary. -Pemetrexed: concomitant use with NSAIDs can reduce the elimination of pemetrexed, therefore caution should be used when administering higher doses of NSAIDs; in patients with mild to moderate renal impairment (creatinine clearance between 45 and 79 ml/min), concomitant administration of pemetrexed with NSAIDs should be avoided for 2 days before and 2 days after administration of pemetrexed.
SIDE EFFECTS
Adverse events reported as possibly related to dexketoprofen in clinical trials (tablet formulation), as well as adverse reactions reported after the marketing of Enantyum oral solution in sachet are included in the table below, grouped by system and listed in order of frequency: Given that plasma C levelsmax of dexketoprofen for the oral solution formulation are higher than those reported for the tablet formulation, a potential increase in the risk of adverse events (gastrointestinal) cannot be excluded .
Haemolymphatic system disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): ---. Very rare (<1/10,000): Neutropenia, thrombocytopenia.
Immune system disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Edema of the larynx. Very rare (<1/10,000): Anaphylactic reactions, including anaphylactic shock.
Metabolism and nutrition disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Anorexia. Very rare (<1/10,000): ---.
Psychiatric disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Insomnia, anxiety. Rare (≥1/10,000 to <1/1,000): ---. Very rare (<1/10,000): ---.
Nervous system disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Headache, dizziness, drowsiness. Rare (≥1/10,000 to <1/1,000): Paraesthesia, syncope. Very rare (<1/10,000): ---.
Eye disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): ---. Very rare (<1/10,000): Blurred vision.
Ear and labyrinth disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Dizziness. Rare (≥1/10,000 to <1/1,000): ---. Very rare (<1/10,000): Tinnitus.
Cardiac disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Palpitations. Rare (≥1/10,000 to <1/1,000): ---. Very rare (<1/10,000): Tachycardia.
Vascular disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Redness. Rare (≥1/10,000 to <1/1,000): Hypertension. Very rare (<1/10,000): Hypotension.
Respiratory, thoracic and mediastinal disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Bradypnea. Very rare (<1/10,000): Bronchospasm, dyspnoea.
Gastrointestinal disorders - Common (≥1/100 to <1/10): Nausea and/or vomiting, abdominal pain, diarrhoea, dyspepsia. Uncommon (≥1/1,000 to <1/100): Gastritis, constipation, dry mouth, flatulence. Rare (≥1/10,000 to <1/1,000): Peptic ulcer, haemorrhage or perforation from peptic ulcer (see section 4.4). Very rare (<1/10,000): Pancreatitis.
Hepatobiliary disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Hepatocellular damage.
Skin and subcutaneous tissue disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Skin rash. Rare (≥1/10,000 to <1/1,000): Urticaria, acne, increased sweating. Very rare (<1/10,000): Stevens Johnson syndrome, toxic epidermal necrolysis (Lyell's syndrome), angioedema, facial edema, photosensitivity reaction, pruritus.
Musculoskeletal and connective tissue disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Back pain. Very rare (<1/10,000): ---.
Renal and urinary disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Acute renal failure, Polyuria. Very rare (<1/10,000): Nephritis or nephrotic syndrome.
Reproductive system and breast disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Menstrual disorder, prostate disease. Very rare (<1/10,000): ---.
General disorders and administration site disorders - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): Fatigue, pain, asthenia, chills, feeling unwell. Rare (≥1/10,000 to <1/1,000): Peripheral edema. Very rare (<1/10,000): ---.
Investigations - Common (≥1/100 to <1/10): ---. Uncommon (≥1/1,000 to <1/100): ---. Rare (≥1/10,000 to <1/1,000): Abnormal liver function tests. Very rare (<1/10,000): ---.
The most commonly observed side effects are gastrointestinal in nature. Peptic ulcers, perforation or gastrointestinal bleeding may occur, sometimes fatal especially in the elderly (see section 4.4 Warnings and precautions for use). Following administration, nausea, vomiting, diarrhoea, flatulence, constipation, dyspepsia, abdominal pain, melena, haematemesis, ulcerative stomatitis, exacerbation of colitis and Crohn's disease have been reported (see section 4.4). Gastritis has been detected less frequently. Edema, hypertension and heart failure have been reported in association with NSAID therapy. As with other NSAIDs, the following side effects may occur: aseptic meningitis, which may occur more in patients with systemic lupus erythematosus or mixed connective tissue disease; haematological reactions (purpura, aplastic and haemolytic anemia, and more rarely agranulocytosis and marrow hypoplasia). Bullous reactions including Stevens Johnson syndrome and toxic epidermal necrolysis (very rare). The results of clinical trials and epidemiological data suggest that the use of some NSAIDs (especially at high doses and for long periods) may be associated with a small increase in the risk of arterial thrombotic events (e.g. myocardial infarction or stroke) (see section 4.4). Reporting of suspected adverse reactions It is important to report suspected adverse reactions after authorization of the drug. It allows continuous monitoring of the benefit/risk ratio of the drug. Healthcare professionals are asked to report any suspected adverse reaction through the national reporting system at http://www.aifa.gov.it/content/segnalazioni-reazioni-avverse.
OVERDOSE
Symptoms resulting from overdose are not known. Similar medicinal products have caused gastrointestinal (vomiting, anorexia, abdominal pain) and neurological disorders (drowsiness, dizziness, disorientation, headache). In case of accidental or excessive intake, immediately adopt adequate symptomatic therapy based on the clinical conditions of the patients. Activated charcoal should be administered within one hour if more than 5 mg/kg has been ingested by an adult or child. Dexketoprofen trometamol can be eliminated by dialysis.
PREGNANCY AND BREASTFEEDING
Dexketoprofen is contraindicated during the third trimester of pregnancy and during breastfeeding (see section 4.3). Pregnancy Inhibition of prostaglandin synthesis may have negative effects on pregnancy and/or the development of the embryo or fetus. Results of epidemiological studies suggest an increased risk of miscarriage and cardiac malformation and gastroschisis after the use of a prostaglandin synthesis inhibitor in early pregnancy. The absolute risk of cardiac malformations was increased from less than 1% to approximately 1.5%. The risk is thought to increase with the dose and duration of therapy. In animals, the administration of prostaglandin synthesis inhibitors has been shown to cause an increase in pre- and post-implantation loss and embryo-foetal mortality. Furthermore, an increased incidence of various malformations, including cardiovascular malformations, has been reported in animals administered prostaglandin synthesis inhibitors during the organogenetic period (see section 5.3). From the 20tha week of pregnancy onwards, the use of dexketoprofen could cause oligohydramnios resulting from fetal renal dysfunction. This condition may be experienced shortly after starting treatment and is usually reversible upon discontinuation of treatment. In addition, there have been reports of constriction of the ductus arteriosus following treatment in the second trimester, the majority of which resolved after treatment discontinuation. Therefore, during the first and second trimester of pregnancy, dexketoprofen should not be administered except when strictly necessary. If dexketoprofen is used by a woman attempting to conceive or during the first and second trimester of pregnancy, the dose and duration of treatment should be kept as low as possible. Following exposure to dexketoprofen for several days from the 20tha week of gestation onwards, antenatal monitoring for oligohydramnios and constriction of the ductus arteriosus should be considered. Treatment with dexketoprofen should be discontinued if oligohydramnios or constriction of the ductus arteriosus occurs. During the third trimester of pregnancy, all prostaglandin synthesis inhibitors may expose the fetus to: - cardiopulmonary toxicity (constriction/premature closure of the ductus arteriosus and pulmonary hypertension), - renal dysfunction (see above); the mother and newborn, at the end of pregnancy, to: - possible prolongation of bleeding time, an anti-aggregating effect which can occur even at very low doses, - inhibition of uterine contractions which lead to delay or prolongation of labour. Breastfeeding It is not known whether dexketoprofen is excreted in breast milk. Its use is contraindicated during breastfeeding (see section 4.3). Fertility As with other NSAIDs, the use of dexketoprofen may damage female fertility and is not recommended for use in women wishing to become pregnant. In the case of women with difficulty conceiving or who are undergoing infertility tests, consider interrupting the administration of dexketoprofen.
EFFECTS ON DRIVING ABILITY
This medicine may cause side effects such as dizziness, visual disturbances or drowsiness. In such cases the ability to react, drive a car or use machinery may be impaired.
OUR PRODUCTS FOR THIS SEASON
-
Curial βeta Dry eye supplement 30 capsules Dr.Tili
Vendor:TilpharmaRegular price €22,50Regular priceUnit price per€22,50Sale price €22,50 -
T - Relaxfast Sleep Supplement 60 Capsules Dr.Tili
Vendor:TilpharmaRegular price €24,50Regular priceUnit price per€24,50Sale price €24,50 -
Face Serum C5 Vitamin C 30ml Dr.Tili Skinlab
Vendor:TilabRegular price €62,50Regular priceUnit price per€62,50Sale price €62,50 -
Dr.Tili Skinlab E15 Vitamin E Face Serum 30ml
Vendor:TilabRegular price €32,50Regular priceUnit price per€32,50Sale price €32,50 -
Vit+ Face Vitamin Cream 50ml Dr.Tili Skinlab
Vendor:TilabRegular price €34,00Regular priceUnit price per€34,00Sale price €34,00 -
Anti-aging Facial Treatment Hyaluronic Acid IAL B3 30ml Dr.Tili Skinlab
Vendor:TilabRegular price €46,00Regular priceUnit price per€46,00Sale price €46,00 -
Body Milk Hydra Milk 200Ml. Dr.Tili Skinlab
Vendor:TilabRegular price €16,90Regular priceUnit price per€16,90Sale price €16,90 -
Facial Cleansing Milk 150ml Dr.Tili Skinlab
Vendor:TilabRegular price €18,90Regular priceUnit price per€18,90Sale price €18,90 -
Soothing Facial Toner 125ml Dr.Tili Skinlab
Vendor:TilabRegular price €14,50Regular priceUnit price per€14,50Sale price €14,50 -
Soothing Face Cream 50ml Dr.Tili Skinlab
Vendor:TilabRegular price €19,50Regular priceUnit price per€19,50Sale price €19,50

















-

ASSISTANCE - TELEPHONE ORDERS
-

SHIPPING
Shipping to Italy 24/48H
Delivery also on Saturday and Sunday
Free over €49.90
Shipping to Europe 24/72H
Free over €80 -

SAFETY
The security of your data is important to us!
We strictly comply with the European GDPR regarding
Privacy and processing of personal data
The payments you make on our site are 100% safe and guaranteed -

RETURNS
Fast returns via DIY portal and 14 days to change your mind.
Immediate and free replacements for incorrect or non-compliant products delivered.


