

Mylan
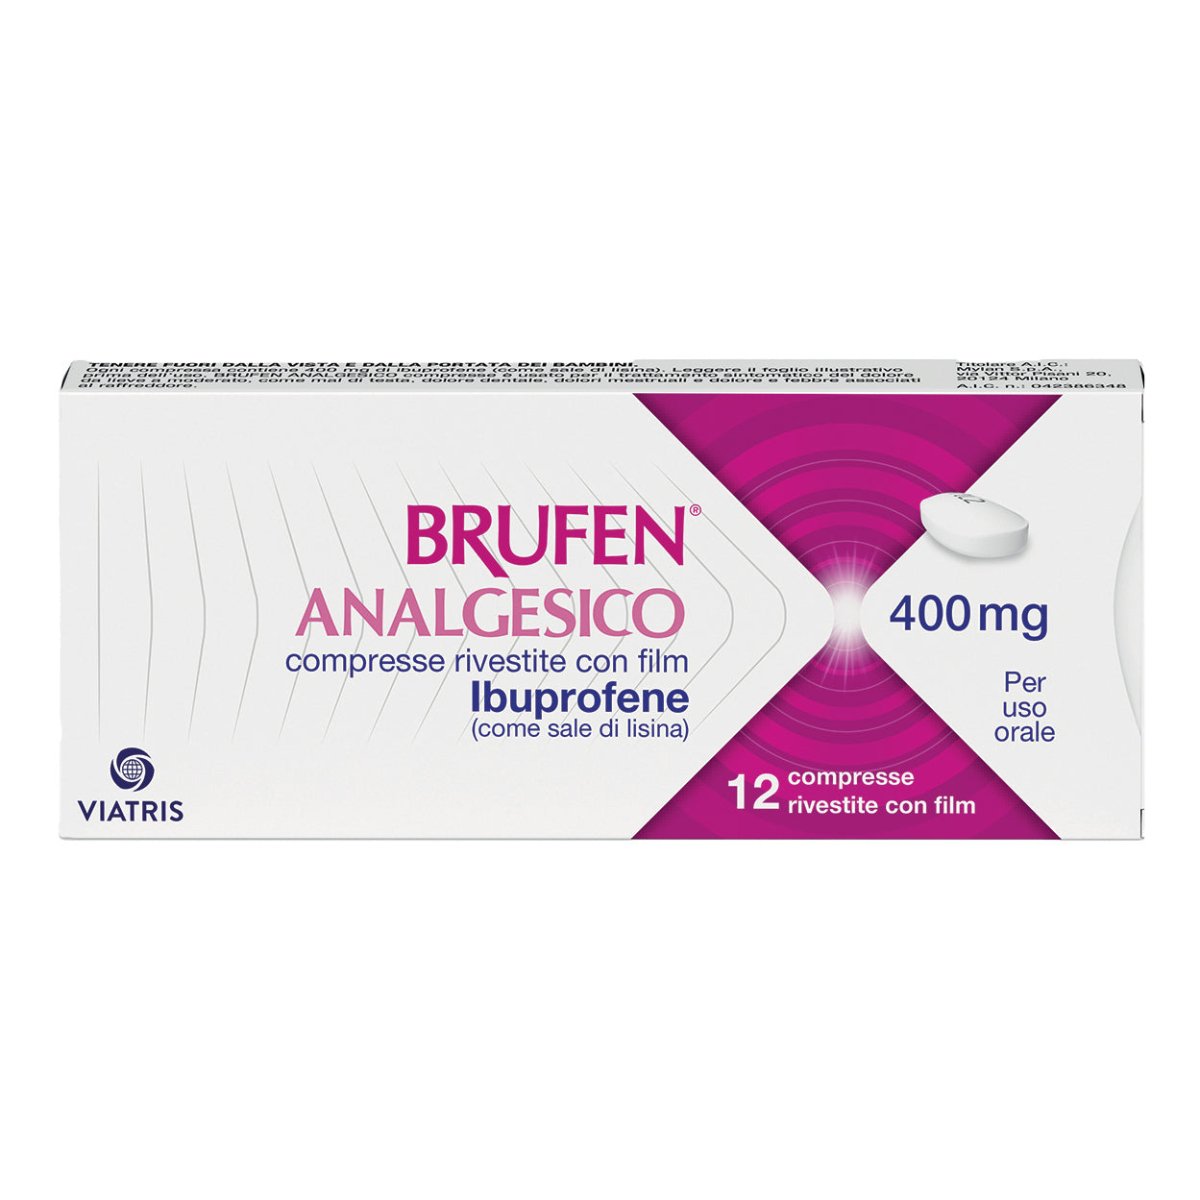
Brufen 400 mg 12 coated tablets
Brufen 400 mg 12 coated tablets

Couldn't load pickup availability

NET WEIGHT OF THE PRODUCT
NET WEIGHT OF THE PRODUCT
12ct
EAN
EAN
042386348
MINSAN
MINSAN
042386348
In compliance with article 118 "authorization of advertising to the public" of the legislative decree of 24 April 2006, number 219
INDICATIONS
For the symptomatic treatment of mild to moderate pain, such as headache, dental pain, menstrual pain and fever, and pain in the common cold.
CONTRAINDICATIONS
Ibuprofen is contraindicated in patients: - with hypersensitivity to the active substance or to any of the excipients listed in section 6.1, - with previous hypersensitivity reactions (e.g. bronchospasm, angioedema, rhinitis, urticaria or asthma) in response to acetylsalicylic acid (ASA) or other non-steroidal anti-inflammatory drugs (NSAIDs), - with the presence or history of peptic ulcer/recurrent haemorrhage (two or more distinct episodes of demonstrated ulceration or bleeding), - with a history of gastrointestinal haemorrhage or perforation related to previous treatment with NSAIDs, - with severe hepatic insufficiency, severe renal insufficiency or severe heart failure (NYHA Class IV) (see section 4.4), - (Only 200 mg) children under 20 kg in weight (approximately 6 years of age) - (Only 400 mg) adolescents weighing less than 40 kg or children under 12 years of age - with cerebrovascular haemorrhage or other types of active haemorrhage, - with unexplained blood formation disorders, - with severe dehydration (caused by vomiting, diarrhea or insufficient fluid intake), - during the last trimester of pregnancy (see section 4.6).
WARNINGS AND PRECAUTIONS FOR USE
Side effects can be minimized by using the lowest effective dose for the shortest time necessary to achieve symptom control (see effects on the gastrointestinal and cardiovascular systems). Caution should be exercised when administering ibuprofen to patients suffering from the following conditions, which may worsen: - congenital disorders of porphyrin metabolism (e.g. acute intermittent porphyria), - coagulation disorders (ibuprofen may prolong the duration of clotting), - directly after major surgery, - systemic lupus erythematosus and mixed connective tissue disease (e.g. increased risk of aseptic meningitis) (see section 4.8), - hypertension and/or heart failure, as renal function may deteriorate (see sections 4.3 and 4.8), - in patients suffering from hay fever, nasal polyps or chronic obstructive respiratory disorders, as there is an increased risk of allergic reactions for them. These may present an asthma attack (so-called analgesic asthma), Quincke's edema or urticaria, - in patients who react with allergies to other substances, since there is also an increased risk of the appearance of hypersensitivity reactions during the use of ibuprofen. Elderly Elderly people have an increased frequency of adverse reactions to NSAIDs, especially gastrointestinal bleeding and perforation, which can be fatal (see section 4.2). Respiratory reactions Bronchospasm may be precipitated in patients suffering from bronchial asthma or allergic diseases or with a history of such diseases. Other NSAIDs The use of ibuprofen with other NSAIDs, including selective cyclo-oxygenase-2 inhibitors, increases the risk of adverse reactions and should be avoided (see section 4.5). Renal effects Renal impairment, as renal function may deteriorate further (see sections 4.3 and 4.8). In general terms, the habitual intake of analgesics, in particular the combination of different analgesic substances, can lead to permanent kidney damage with the risk of renal failure (analgesic nephropathy). This risk may increase under physical exertion associated with salt loss and dehydration. Therefore it must be avoided. There is a risk of renal impairment in dehydrated children and adolescents. Hepatic effects Hepatic dysfunction (see sections 4.3 and 4.8). It is appropriate to discontinue ibuprofen therapy when deterioration of liver function occurs concomitantly with its administration. After stopping treatment, the state of health usually normalizes. Occasional blood glucose monitoring is also appropriate. Cardiovascular and cerebrovascular effects Particular caution is required (discuss with your doctor or pharmacist) before starting treatment in patients with a history of hypertension and/or heart failure, because fluid retention, hypertension and edema have been reported in association with NSAID therapy. Patients suffering from uncontrolled hypertension (NYHA class II-III), congestive heart failure, established ischemic heart disease, peripheral arterial disease and/or cerebrovascular disease should be treated with ibuprofen only after careful evaluation and high doses (2400 mg/day) should be avoided. Careful consideration should also be exercised before starting long-term treatment in patients with risk factors for cardiovascular events (e.g. hypertension, hyperlipidemia, diabetes mellitus or smoking), particularly if high doses of ibuprofen (2400 mg/day) are required. Clinical studies suggest that the use of ibuprofen, especially at a high dose (2400 mg/day) and for long-term treatments, may be associated with a slight increase in the risk of arterial thrombotic events (for example myocardial infarction or stroke). In general, epidemiological studies do not indicate that low doses of ibuprofen (e.g. ≤1200 mg/day) are associated with an increased risk of arterial thrombotic events. Alteration of female fertility There is some evidence that drugs that inhibit the synthesis of cyclooxygenase/prostaglandins can cause alterations in female fertility through an effect on ovulation. This is reversible after discontinuation of treatment (see section 4.6). Gastrointestinal safety NSAIDs should be administered with caution in patients with a history of gastrointestinal disease (ulcerative colitis, Crohn's disease), as these conditions may be exacerbated (see section 4.8). Gastrointestinal bleeding, ulceration or perforation, which may be fatal, have been reported during treatment with all NSAIDs, at any time during therapy, with or without warning symptoms or previous history of serious gastrointestinal events. In patients with a history of ulcer, especially if complicated by haemorrhage or perforation (see section 4.3), and in the elderly, the risk of gastrointestinal haemorrhage, ulceration or perforation is greater with increasing doses of NSAIDs. These patients should start treatment with the lowest available dose. Concomitant use of protective agents (e.g. misoprostol or proton pump inhibitors) should be considered both for these patients and for patients concomitantly taking low doses of acetylsalicylic acid or other drugs that may increase the risk of gastrointestinal events (see below and section 4.5). Patients with a history of gastrointestinal toxicity, particularly if elderly, should report any unusual gastrointestinal symptoms (especially gastrointestinal haemorrhage) particularly in the initial stages of treatment. Caution is required when treating patients taking concomitant medications that may increase the risk of ulceration or haemorrhage, such as oral corticosteroids, anticoagulants such as warfarin, selective serotonin reuptake inhibitors or antiplatelet agents such as acetylsalicylic acid (see section 4.5). When gastrointestinal bleeding or ulceration occurs in patients taking ibuprofen, treatment should be discontinued. Severe skin reactions Serious skin reactions, some of them fatal, such as exfoliative dermatitis, Steven - Johnson syndrome and toxic epidermal necrolysis, have been reported very rarely in association with the use of NSAIDs (see section 4.8). In the early stages of therapy, patients appear to be at higher risk of these reactions: in fact, the onset of the reaction occurs in most cases within the first month of treatment. Acute generalized exanthematous pustulosis (PEAG) has been reported in connection with ibuprofen-containing medicinal products. The use of ibuprofen should be discontinued at the first appearance of skin rash, mucosal lesions or any other sign of hypersensitivity. Exceptionally, chickenpox can cause severe skin reactions and soft tissue infectious complications. So far, the contributory role of NSAIDs in the worsening of these infections cannot be excluded. Therefore, it is recommended to avoid the use of ibuprofen in case of chickenpox. Masking the symptoms of underlying infections BRUFEN ANALGESICO may mask the symptoms of infection, which could delay the initiation of adequate treatment and therefore worsen the outcome of the infection. This has been observed in community-acquired bacterial pneumonia and bacterial complications of chickenpox. When BRUFEN ANALGESIC is administered for the relief of fever or pain related to infection, monitoring of the infection is recommended. In non-hospital settings, the patient should seek medical attention if symptoms persist or worsen. Other observations In rare cases, severe acute hypersensitivity reactions (e.g. anaphylactic shock) have been observed. Therapy should be suspended at the first signs of a hypersensitivity reaction after taking/administrating ibuprofen. Medical procedures appropriate to the symptoms must be performed by specialized personnel. Ibuprofen may temporarily inhibit platelet function (aggregation of thrombocytes). It is therefore recommended to carefully monitor patients with coagulation disorders. In prolonged administration of ibuprofen, regular monitoring of liver parameters, renal function and blood cell counts is recommended. Prolonged use of any type of pain reliever for headaches can cause them to get worse. If such a situation occurs or is suspected, medical advice should be obtained and treatment should be discontinued. The diagnosis of medication-overuse headache should be suspected in patients who have frequent or daily headaches despite (or because of) regular use of headache medications. Medication overuse headache should not be treated by increasing the dosage of the medicine. During treatment with ibuprofen, some cases with symptoms of aseptic meningitis, such as neck stiffness, headache, nausea, vomiting, fever or disorientation, have been observed in patients with pre-existing autoimmune disorders (such as systemic lupus erythematosus, mixed connective tissue disease). Alcohol consumption should be avoided as it can intensify the side effects of NSAIDs, especially those relating to the gastrointestinal tract or central nervous system. Patients taking ibuprofen should report signs or symptoms of gastrointestinal ulceration or bleeding, blurred vision or other ocular symptoms, skin rash, weight gain, or edema to their doctor. If vision problems, blurred vision, scotoma or malfunction of color perception appear, treatment must be stopped.
INTERACTIONS
The use of ibuprofen should be avoided in association with: Acetylsalicylic acid Concomitant administration of ibuprofen and acetylsalicylic acid is generally not recommended due to the potential for increased side effects. Experimental data suggest that ibuprofen can competitively inhibit the effect of low-dose acetylsalicylic acid on platelet aggregation when the two drugs are administered simultaneously. Although there are uncertainties regarding the extrapolation of these data to the clinical situation, the possibility cannot be excluded that regular, long-term use of ibuprofen may reduce the cardioprotective effect of acetylsalicylic acid at low doses. No relevant clinical effects are considered likely following occasional use of ibuprofen (see section 5.1). Other NSAIDs including salicylates and selective cyclooxygenase-2 inhibitors: avoid the concomitant use of two or more NSAIDs, because it may increase the risk of gastrointestinal ulcers and bleeding due to a synergistic effect (see section 4.4). Anticoagulants. NSAIDs may increase the effects of anticoagulants, such as warfarin (see section 4.4). Diuretics, ACE inhibitors, beta blockers and angiotensin II antagonists: NSAIDs can reduce the effect of diuretics and other antihypertensive drugs. In some patients with compromised renal function (e.g. dehydrated patients or elderly patients with compromised renal function) co-administration of an ACE inhibitor, a beta blocker or an angiotensin II antagonist and agents that inhibit the cyclooxygenase system may result in further deterioration of renal function, including acute renal failure, which is generally reversible. Therefore, the combination should be administered with caution, especially in elderly patients. Patients should be adequately hydrated and consideration should be given to monitoring renal function after initiation of concomitant therapy and on a regular basis thereafter. Potassium-sparing diuretics: concomitant administration of ibuprofen and potassium-sparing diuretics may lead to hyperkalemia (monitoring of serum potassium is recommended). Corticosteroids: increased risk of adverse reactions, especially of the gastrointestinal tract (ulceration or gastrointestinal haemorrhage) (see section 4.4). Antiplatelet agents and selective serotonin reuptake inhibitors (SSRIs): increased risk of gastrointestinal bleeding (see section 4.4) Digoxin: NSAIDs can exacerbate heart failure, reduce glomerular filtration rate and increase plasma digoxin levels. A control of serum digoxin is not required, as a rule, in correct use (maximum 4 days). Phenytoin: Concomitant use of ibuprofen with phenytoin preparations may increase serum phenytoin levels. A control of serum phenytoin is not required, as a rule, in correct use (maximum 4 days). Lithium: There is evidence of potential increases in plasma lithium levels. A control of serum lithium is not required, as a rule, in correct use (maximum 4 days). Methotrexate: Administration of ibuprofen within 24 hours before administration of methotrexate may lead to increased methotrexate concentrations and increased toxic effects. Cyclosporine: the risk of a harmful effect on the kidneys due to ciclosporin is increased by the co-administration of some NSAIDs. This effect cannot also be excluded due to the association of ciclosporin with ibuprofen. Mifepristone. NSAIDs should not be used for 8-12 days after administration of mifepristone, because NSAIDs may reduce the effect of mifepristone. Sulfinpyrazone: Medicines containing sulfinpyrazone may delay the excretion of ibuprofen. Probenecid: Medicinal products containing probenecid may reduce the excretion of NSAIDs and may increase their serum concentrations. Tacrolimus: possible increased risk of nephrotoxicity if NSAIDs are co-administered with tacrolimus. Zidovudine: increased risk of hematological toxicity when NSAIDs are co-administered with zidovudine. A blood cell count is recommended 1-2 weeks after starting co-administration. There are indications of an increased risk of haemarthrosis and haematoma in HIV-positive patients with haemophilia receiving concomitant treatment with zidovudine and ibuprofen. Sulfonylureas: NSAIDs can both increase and decrease the hypoglycaemic effect of sulphonylureas. Caution is advised in case of simultaneous treatment. Quinolone antibiotics: Animal data indicate that NSAIDs may increase the risk of seizures associated with quinolone antibiotics. Patients taking NSAIDs and quinolones may have an increased risk of developing seizures. Alcohol, bisphosphonates, oxpentifylline (pentoxyfylline) and sulfinpyrazone: may potentiate gastrointestinal effects and the risk of bleeding or ulceration. Baclofen: increased toxicity of baclofen.
SIDE EFFECTS
Possible side effects are those seen with ibuprofen acid. Side effects are mostly dose-dependent and vary individually. In particular, the risk of gastrointestinal bleeding depends on the dose and duration of treatment. For other risk factors, see section 4.4. The following side effects are related to short-term use of low-dose ibuprofen (up to 1200 mg per day for mild to moderate pain and fever). Other undesirable effects may occur with treatments for other indications or prolonged use. The side effects associated with ibuprofen are listed in the table below according to system organ classification and frequency. Frequencies are defined as very common (≥ 1/10), common (≥ 1/100 and < 1/10), uncommon (≥ 1/1000 and < 1/100), rare (≥ 1/10,000 and < 1/1000), very rare (< 1/10,000) and not known (cannot be estimated from the available data). For each frequency, side effects are listed in descending order of frequency.
Classification by systems and organs | Frequency | Side effects
Pathologies of the blood and lymphatic system | Very rare | haematopoietic pathologies¹
Immune system disorders | Uncommon | hypersensitivity reactions with urticaria and itching²
Very rare | severe hypersensitivity reactions. Symptoms may include: swelling of the face, tongue and larynx, edema, dyspnoea, tachycardia, hypotension (anaphylaxis, angioedema or severe shock)²
Psychiatric disorders | Rare | confusion, hallucinations
Not known | psychotic disorders, depression
Nervous system disorders | Municipality | headache, drowsiness, dizziness, fatigue, agitation, dizziness, insomnia, irritability
Very rare | aseptic meningitis
Eye disorders | Not known | amblyopia4, blurred vision4, reduced vision4
Ear and labyrinth disorders | Rare | Tinnitus
Cardiac disorders | Very rare | Palpitations, myocardial infarction, acute pulmonary edema
Not known | heart failure, edema
Vascular pathologies | Not known | arterial hypertension
Respiratory, thoracic and mediastinal disorders | Uncommon | Rhinitis
Very rare | Asthma exacerbation
Not known | Respiratory tract reactions such as bronchospasm, asthma or dyspnoea²
Gastrointestinal disorders | Very common | Heartburn, abdominal pain, nausea, dyspepsia, diarrhea, flatulence, constipation and vomiting5
Municipality | Peptic ulcer6, perforation or gastrointestinal bleeding6, melena, hematemesis, ulcerative stomatitis, colitis
Uncommon | gastritis
Very rare | esophagitis, pancreatitis, intestinal narrowing
Not known | exacerbation of colitis and Crohn's disease7
Hepatobiliary disorders | Very rare | liver dysfunction, liver damage, especially in long-term use, liver failure, acute hepatitis and jaundice8
Skin and subcutaneous tissue disorders | Uncommon | Photosensitivity, skin rash²
Very rare | severe forms of soft tissue skin reactions may occur during chickenpox infections, necrotizing fasciitis, exfoliative dermatitis, bullous reactions, including Steven-Johnson syndrome, erythema multiforme, and toxic epidermal necrolysis²
Not known | Alopecia9, adverse reaction with eosinophilia and systemic symptoms (DRESS syndrome). Acute generalized exanthematous pustulosis (PEAG).
Renal and urinary disorders | Uncommon | development of edema, especially in patients with arterial hypertension or renal failure, nephrotic syndrome, interstitial nephritis which may be associated with renal failure10
Rare | renal papillary necrosis10
Very rare | Acute renal failure10, dysuria
Reproductive system and breast disorders | Not known | menstrual disorders
Diagnostic tests | Rare | increased blood urea nitrogen, transaminases and alkaline phosphatase, decreased hemoglobin and hematocrit, inhibition of platelet aggregation, decreased serum calcium, increased serum uric acid
Not known | prolongation of bleeding time11
Description of selected adverse reactions ¹ Examples include anemia, leukopenia, thrombocytopenia, pancytopenia, and agranulacytosis. First signs: fever, sore throat, mouth ulcers, flu-like symptoms, symptoms of severe fatigue, nose and skin bleeding. ² Hypersensitivity reactions: may include (a) non-specific allergic reactions and anaphylaxis, (b) respiratory tract reactions including asthma, asthma exacerbation, bronchospasm and dyspnoea, or (c) various skin reactions, including urticaria, exanthema and purpura, sometimes associated with pruritus. Angioedema and, in rare cases, exfoliative and bullous dermatitis, including toxic epidermal necrolysis, Stevens-Johnson syndrome and erythema multiforme, have been reported. Some reactions including meningeal irritation and lethargy are considered to be associated with hypersensitivity reactions. Systemic lupus erythematosus and other collagen disorders are risk factors for severe cases of generalized hypersensitivity reactions. General hypersensitivity reactions are uncommon. Symptoms may include fever with rash, abdominal pain, headache, nausea and vomiting, signs of liver damage, and even meningeal symptoms. In rare cases, ibuprofen can lead to bronchospasm in predisposed individuals. ³ The pathogenic mechanism of drug-induced aseptic meningitis is not fully understood. However, the data available on NSAID-related aseptic meningitis suggest a hypersensitivity reaction (due to the temporal correlation between the administration of the medicine and the disappearance of symptoms after discontinuation of treatment). Isolated cases of symptoms of aseptic meningitis such as neck stiffness, headache, vomiting, fever and disorientation have been observed during treatment with ibuprofen in patients with pre-existing autoimmune diseases (systemic lupus erythematosus and mixed connective tissue disorders). 4 Reversible effects have been observed. 5 The most common side effects are gastrointestinal side effects. 6 Not commonly fatal, especially in elderly patients. See Special warnings and precautions for use. 7 see paragraph 4.4 8 Hepatotoxic reactions may occur as part of generalized hypersensitivity reactions. 9 Reversible alopecia has been reported in black women. 10 Especially for prolonged use, associated with elevated serum urea concentrations, decreased urine excretion and edema. Includes papillary necrosis. 11 Ibuprofen may prolong bleeding time at doses greater than 1000 mg per day. Clinical studies and epidemiological data suggest that the use of ibuprofen, especially at high doses (2400 mg per day) and for prolonged periods, may be associated with a slight increase in the risk of arterial thrombotic events (e.g. myocardial infarction or stroke) (see section 4.4). Reporting of suspected adverse reactions Reporting suspected adverse reactions that occur after authorization of the medicine is important, as it allows continuous monitoring of the benefit/risk balance of the medicine. Healthcare professionals are asked to report any suspected adverse reactions via the national reporting system at https://www.aifa.gov.it/content/segnalazioni-reazioni-avverse.
OUR PRODUCTS FOR THIS SEASON
-
Curial βeta Dry eye supplement 30 capsules Dr.Tili
Vendor:TilpharmaRegular price €22,50Regular priceUnit price per€22,50Sale price €22,50 -
T - Relaxfast Sleep Supplement 60 Capsules Dr.Tili
Vendor:TilpharmaRegular price €24,50Regular priceUnit price per€24,50Sale price €24,50 -
Face Serum C5 Vitamin C 30ml Dr.Tili Skinlab
Vendor:TilabRegular price €62,50Regular priceUnit price per€62,50Sale price €62,50 -
Dr.Tili Skinlab E15 Vitamin E Face Serum 30ml
Vendor:TilabRegular price €32,50Regular priceUnit price per€32,50Sale price €32,50 -
Vit+ Face Vitamin Cream 50ml Dr.Tili Skinlab
Vendor:TilabRegular price €34,00Regular priceUnit price per€34,00Sale price €34,00 -
Anti-aging Facial Treatment Hyaluronic Acid IAL B3 30ml Dr.Tili Skinlab
Vendor:TilabRegular price €46,00Regular priceUnit price per€46,00Sale price €46,00 -
Body Milk Hydra Milk 200Ml. Dr.Tili Skinlab
Vendor:TilabRegular price €16,90Regular priceUnit price per€16,90Sale price €16,90 -
Facial Cleansing Milk 150ml Dr.Tili Skinlab
Vendor:TilabRegular price €18,90Regular priceUnit price per€18,90Sale price €18,90 -
Soothing Facial Toner 125ml Dr.Tili Skinlab
Vendor:TilabRegular price €14,50Regular priceUnit price per€14,50Sale price €14,50 -
Soothing Face Cream 50ml Dr.Tili Skinlab
Vendor:TilabRegular price €19,50Regular priceUnit price per€19,50Sale price €19,50

















-

ASSISTANCE - TELEPHONE ORDERS
-

SHIPPING
Shipping to Italy 24/48H
Delivery also on Saturday and Sunday
Free over €49.90
Shipping to Europe 24/72H
Free over €80 -

SAFETY
The security of your data is important to us!
We strictly comply with the European GDPR regarding
Privacy and processing of personal data
The payments you make on our site are 100% safe and guaranteed -

RETURNS
Fast returns via DIY portal and 14 days to change your mind.
Immediate and free replacements for incorrect or non-compliant products delivered.


